D2393 is the CDT code for a tooth-colored composite filling that restores three surfaces of a premolar or molar, most often an MOD.
- When to use: A direct composite on a back tooth restores exactly three surfaces, such as MOD, MOB, or ODL.
- When not to use: Two surfaces is D2392, four or more is D2394, a three-surface amalgam is D2160, and a buildup under a planned crown is D2950.
- Billing note: Many plans pay D2393 at the D2160 amalgam allowable, so show the patient that gap on a pre-treatment estimate.
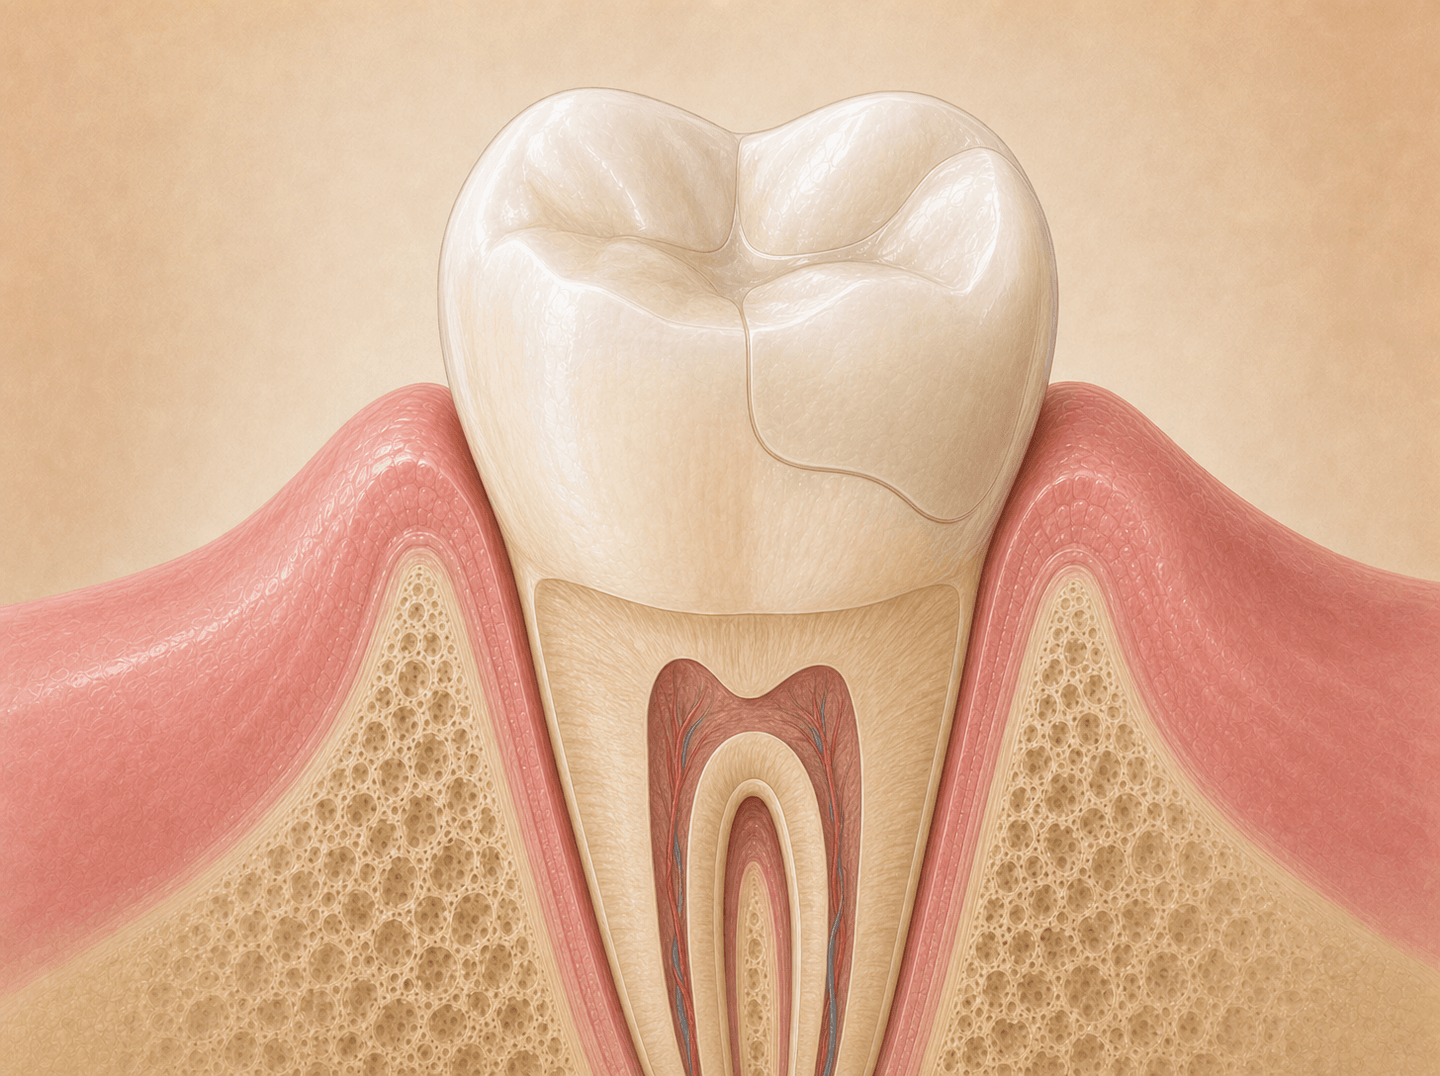
What D2393 covers
D2393 reports a resin-based composite restoration covering three surfaces of a posterior tooth (premolar or molar). The code includes the material, placement, contouring, finishing, and occlusal adjustment.
The three surfaces can be any combination of M (mesial), O (occlusal), D (distal), B (buccal), and L (lingual). MOD is the most common. MOB, MOL, ODB, ODL, OBL, MDB, and MDL are less common but valid.
It does not cover:
- One-surface posterior composites. Use D2391.
- Two-surface posterior composites. Use D2392.
- Posterior composites on four or more surfaces. Use D2394.
- Anterior composites. Use D2332 for three surfaces.
- Amalgam restorations. Use D2160 for three surfaces.
- Indirect inlays or onlays. Use the D2510 series for inlays and the D2542 series for onlays.
- Core buildups under crowns. Use D2950.
When to bill D2393
Bill D2393 when a premolar or molar has a carious lesion or failing restoration involving exactly three surfaces, and those surfaces are restored with resin-based composite. The three surfaces may be restored and shaped in continuity, or as a single restoration involving three discrete walls.
Billing D2393 on a four-surface case underbills the procedure and creates a chart-claim inconsistency on audit.
Surface count and chart-to-claim consistency
The surface count determines the code. Common three-surface combinations:
- MOD (mesial-occlusal-distal): the most common, on premolars and molars. Replaces decay or a failing restoration that extends through both proximal contacts and across the occlusal.
- MOB or MOL: mesial decay that wraps onto the buccal or lingual surface as well as the occlusal.
- ODB or ODL: the distal-side equivalent of MOB and MOL.
- OBL: occlusal extending to both buccal and lingual. Uncommon as a standalone three-surface case.
Record the specific surfaces on both the chart and the claim. The designation tells the carrier what was restored and lets it apply frequency and downgrade rules correctly. Match the letters to the code:
- D2391: one letter (M, O, D, B, or L).
- D2392: two letters.
- D2393: three letters.
- D2394: four or five letters.
D2393 with a four-letter surface designation is flagged for code-surface mismatch, the most common preventable rejection on this code. The chart and claim must also agree: “MOD” in the chart and MODB on the claim will not pass audit, and the reverse underbills with the same audit risk.
A frequent cause is a surface field that defaults to MOD and isn’t changed when the case is actually MOB or ODL. Most practice management systems can be configured to require a surface count that matches the selected code.
The alternate-benefit downgrade at the three-surface level
Many plans pay posterior composites at the matching amalgam allowable, as they do on D2391 and D2392. For a three-surface composite, that is D2160.
How it works:
- The office submits D2393 at the composite fee.
- The carrier applies the alternate-benefit clause and pays at the D2160 allowable.
- What the patient owes depends on the contract. Out of network, or where the PPO contract permits it, the patient owes the difference between the composite office fee and the amalgam allowable. Under many in-network PPO contracts, the office writes off down to its contracted composite allowable and bills the patient only the difference between that allowable and the amalgam allowable.
The gap is larger at three surfaces than at one or two, because composite fees rise faster than amalgam fees. A pre-treatment estimate showing the D2160 allowable prevents most patient-responsibility disputes.
Top reasons D2393 gets denied or downgraded
- Surface-count miscoding. D2393 billed on a four-surface case (D2394) or a two-surface case (D2392). The carrier may pay at the correct allowable, deny pending clarification, or request a chart audit on repeat offenders.
- Alternate-benefit downgrade. The most common scenario, and not a denial. The plan pays at the D2160 allowable. Check the PPO contract before billing the patient, because many in-network contracts require writing off part of the difference.
- Frequency limit on the same tooth. Most plans pay one restoration per tooth surface per benefit year or per two years, counted across the patient’s full insurance history, not just visits to your office, so pull the restorative history before treatment planning. A narrative documenting recurrent decay or failure of the prior restoration usually clears it.
- Audit pend for clinical photos. A small number of carriers request pre-op or intra-op photos on three-surface composites. Submit what the chart has.
- Crown-versus-restoration question. If the carrier judges the tooth should have been crowned (extensive structural loss, cusp involvement, fracture risk), the claim can pend for clinical justification. A narrative explaining the conservative approach and the patient’s preference for a direct restoration usually clears it.
Documentation that supports the claim
The claim needs:
- Date of service.
- Tooth number.
- Three-letter surface designation.
- A pre-op radiograph for some carriers (often requested on audit, not upfront).
In the patient record, document:
- The clinical reason for each surface (caries, fracture, failing prior restoration).
- Surfaces restored, listed individually.
- Material used.
- Liner or base, if placed.
- Occlusion adjusted and verified.
- Patient instructions and post-op expectations.
“MOD filling on #14” is enough if the preceding clinical note documents the diagnostic finding. “Filling, #14” alone doesn’t pass audit.
Example case
A 44-year-old patient presents at recall with a failing MOD amalgam on tooth #18. The pre-op periapical shows marginal breakdown on the distal and recurrent decay under the mesial margin. The dentist removes the amalgam, finds caries across all three surfaces, and places a three-surface composite.
Billing steps:
- Verify benefits and the plan’s posterior composite coverage. Pull the D2160 allowable if the plan downgrades.
- Submit D2393 with surface designation MOD on the date of service.
- If the prior restoration was placed less than 24 months ago, add a narrative: “Replacement of failing MOD amalgam on #18. Recurrent decay detected under mesial margin on pre-op periapical. Marginal breakdown on distal. New composite placed.”
- The carrier processes per the plan’s benefits.
If the plan covers posterior composites at composite rates, the claim pays at the D2393 allowable and the patient owes the standard coinsurance. If the plan downgrades, the claim pays at the D2160 allowable, and the patient owes coinsurance on that amount plus whatever share of the composite-to-amalgam gap the contract allows the office to bill.
FAQs
- What's the difference between D2391, D2392, D2393, and D2394?
- Surface count. All four are posterior composite codes: D2391 is one surface, D2392 is two, D2393 is three, and D2394 is four or more. The surfaces are M, O, D, B, and L. A three-surface restoration is most often MOD but can be any three-surface combination.
- Why did the carrier pay D2393 at the amalgam allowable?
- The plan has an alternate-benefit clause. It considers a three-surface amalgam (D2160) functionally adequate, so it pays D2393 at the D2160 allowable. This is plan language, not a denial. Out of network, or where the contract permits it, the patient owes the difference between the composite office fee and the amalgam allowable. Many in-network PPO contracts require the office to write off down to its contracted composite allowable, so the patient owes only the gap between that allowable and the amalgam allowable, plus any coinsurance or deductible. Billing the full office-fee difference there is improper balance billing.
- When does a case become D2394 instead of D2393?
- When the restoration involves four or more surfaces. An MODB (mesial-occlusal-distal-buccal) or MODL (mesial-occlusal-distal-lingual) restoration is D2394. The allowables differ, so document the surfaces actually restored and bill the code that matches.
- Why did the carrier ask for clinical photos on D2393?
- To confirm the restoration actually covered three surfaces and wasn't a two-surface case overbilled. A small number of carriers audit three-surface composites this way. Submit the pre-op periapical and any intra-op photos taken before placement.
- Can D2393 be billed with a buildup (D2950) on the same tooth?
- Rarely. D2950 is a core buildup for crown retention, not a restoration. If the tooth will be crowned and the buildup supports the crown, bill D2950 alone. If the treatment stops at the composite, bill D2393 alone. Billing both on the same tooth and date is unusual and typically triggers a clarification request.
Related codes
Need help billing this code?
We handle D2393 claims daily.
If your team is spending time on denials, narratives, or carrier follow-up for this code, our outsourced dental insurance billing service can take it off your plate. We submit the claims, post what comes back, and follow up on anything unpaid.
“Claims, posting, denials, all of it gets handled, and it costs far less than hiring another employee. My front desk got hours of their week back, and honestly I just don't think about billing anymore.”
CDT codes are maintained by the American Dental Association. This page is an editorial billing guide, not the official ADA code descriptor. Verify current coverage policies with each carrier before submitting claims.