D1354 is the CDT code for applying a medicament, usually silver diamine fluoride, to stop an active cavity on one tooth without drilling.
- When to use: The treated tooth has an active, non-symptomatic cavity, and each treated tooth is billed as its own unit.
- When not to use: SDF on a sound surface for prevention is D1355, and whole-mouth fluoride varnish or gel is D1206 or D1208.
- Billing note: Many Medicaid programs cap D1354 per tooth, so track each tooth's applications and verify the plan's cap before treating.
What D1354 covers
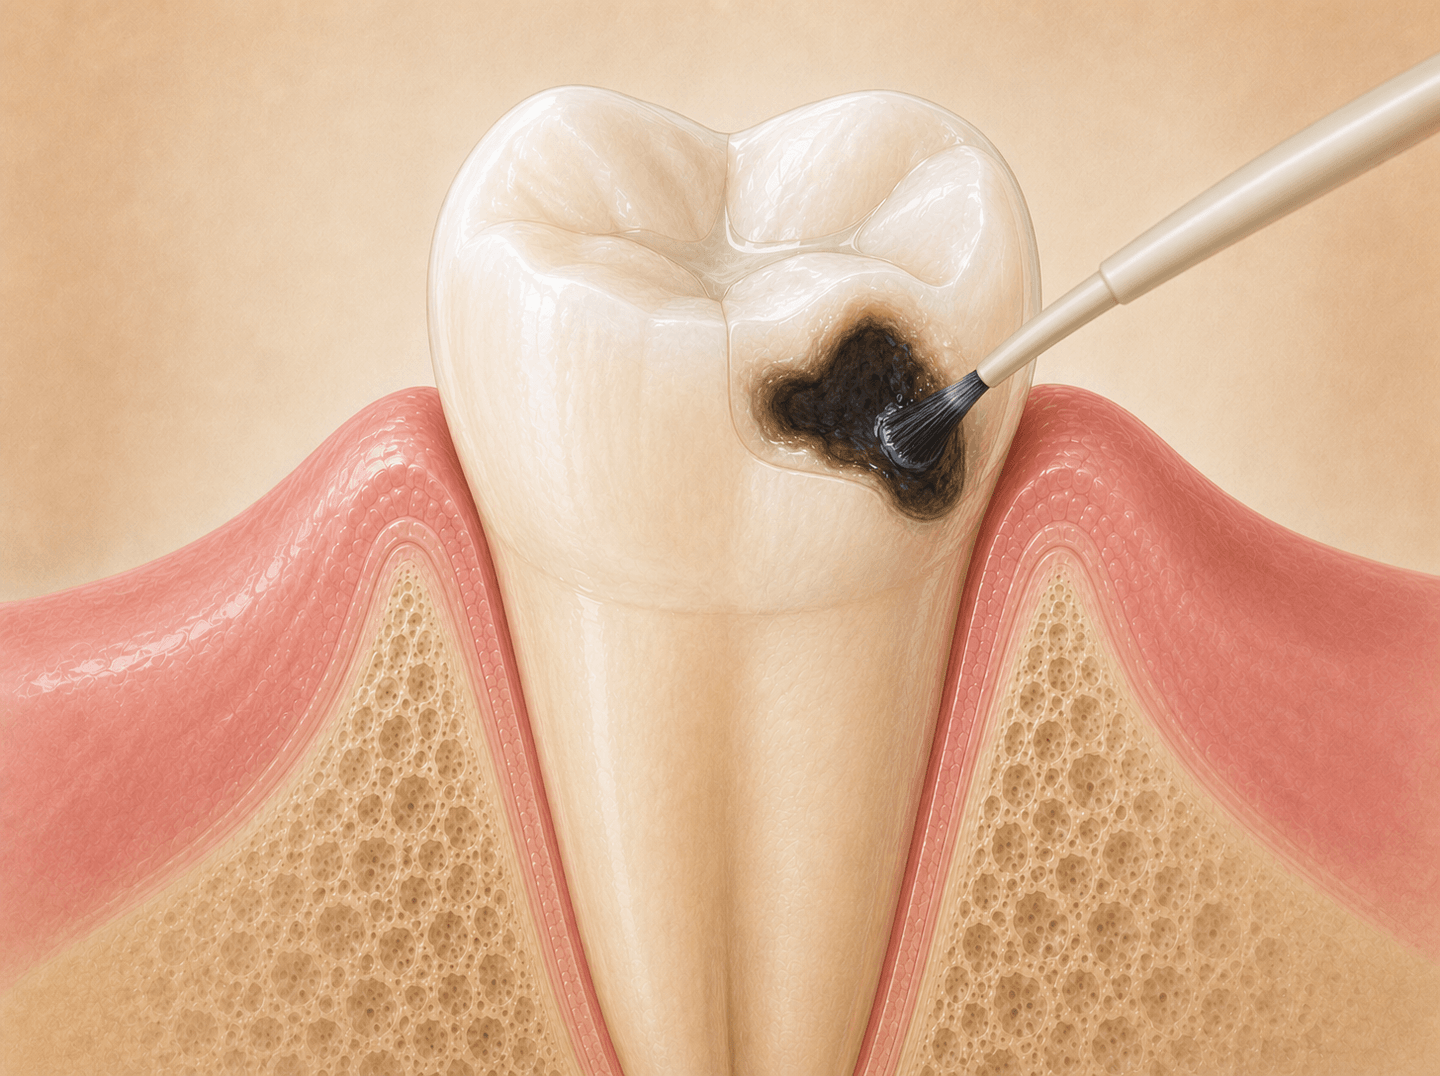
D1354 reports the topical application of a caries-arresting medicament to a tooth with an active, non-symptomatic carious lesion. The medicament is painted onto the lesion to stop or slow the decay, without drilling out tooth structure and without placing a restoration. Silver diamine fluoride (SDF) is the most common medicament, but the code is written around the clinical action, not the product.
Two things define the code. The purpose is arrest: an existing, active cavity that the medicament halts. The scope is one tooth, so a visit that treats several teeth produces several units of D1354.
The code covers the medicament application only. The exam that found the decay, any radiographs, and any restoration placed later are separate procedures with their own codes.
When to bill D1354
Bill D1354 when a caries-arresting medicament, usually SDF, is applied to a tooth with an active, non-symptomatic carious lesion to stop the decay without restoring the tooth. Common situations:
- A pediatric patient with active decay who cannot yet tolerate, or whose family wants to defer, conventional restorative treatment.
- A geriatric or special-needs patient where drilling and restoration are difficult, and arresting the lesion is the practical goal.
- An active lesion the office is stabilizing while the patient waits for a restorative appointment.
- Root-surface or other lesions on patients at high risk where arrest is the clinical plan.
What D1354 is not
- A caries-preventive medicament (D1355). This is the most common miscode. D1355 is applied to a sound or at-risk surface to prevent decay; D1354 treats decay that already exists. See the next section.
- A topical fluoride treatment. D1206 (fluoride varnish) and D1208 (other topical fluoride, excluding varnish) are whole-mouth preventive applications reported once per visit. SDF applied to arrest a specific cavity is D1354, not a fluoride code, even though SDF contains fluoride.
- A definitive restoration. SDF arrests the lesion; it does not fill or rebuild the tooth. A restoration placed later has its own code. The “interim” in the code name marks it as a holding measure, not the final fix.
- Enamel regeneration (D2991). D2991 reports a scaffold-based application that guides hydroxyapatite regeneration on an early lesion. It is classified as restorative and is a different clinical action than arresting an active cavity in place.
- Treatment of a symptomatic tooth. D1354 is scoped to non-symptomatic lesions. A tooth treated for pain or infection points toward different diagnostic and treatment codes.
D1354 vs. D1355: the distinction that drives the code
D1354 and D1355 are both per-tooth medicament codes, both can use SDF, and the products can be physically identical. The code follows the clinical intent on the treated tooth.
- D1354 is arrest. There is an active carious lesion on the tooth, and the medicament is applied to stop it from progressing.
- D1355 is prevention. The surface is sound or at risk, and the medicament is applied to prevent decay or support remineralization in a high-caries-risk patient.
Per tooth, not per visit
D1354 is reported per tooth. Each tooth treated is its own unit, tied to its own tooth number and chart entry. This is the opposite of D1206 and D1208, which are reported once per visit no matter how many teeth are coated.
- SDF on four active lesions on four teeth supports four units of D1354, each documented separately.
- Posting a single D1354 for a multi-tooth SDF appointment underbills the work.
- Each unit needs its own tooth number on the claim and a chart note naming the lesion on that tooth. One tooth number with a quantity of four, or four lines with no per-tooth findings, is harder to defend on review.
Set up the PMS to prompt for a tooth number on D1354 and to post a multi-tooth visit as multiple units.
Coverage reality: Medicaid-first, commercial uneven
SDF coverage grew out of public health programs, and the coverage map still reflects that.
- Medicaid and CHIP. Many state Medicaid and CHIP programs cover D1354. A common structure is a per-tooth lifetime cap (two applications per tooth shows up frequently) and sometimes an age limit. The rules are set state by state, so the program’s own policy governs.
- Commercial plans. Coverage is uneven. Some commercial plans cover D1354 as a preventive benefit, some cover it only for children, some apply frequency or age limits, and some exclude it. There is no single commercial-market rule to assume.
- Patient-pay. When a plan excludes D1354, it is usually a low-cost procedure relative to a restoration, which is part of why patients accept it. On participating Medicaid and other participating plans, confirm the patient-billable rules before charging, because balance-billing limits may apply.
Documentation that supports the claim
For each tooth treated, the note should capture:
- The tooth and the lesion. Tooth number and the active carious lesion on it, including surface and a brief description. This is the line that separates D1354 (active decay) from D1355 (sound surface).
- The medicament. That a caries-arresting medicament was applied, and which one (usually silver diamine fluoride).
- The clinical intent. That the purpose was to arrest the lesion, not to restore the tooth or prevent decay on a sound surface.
- The interim nature. Whether a restoration is planned, monitoring is planned, or arrest is the endpoint for that tooth.
- Patient or guardian acknowledgment of staining. SDF darkens the arrested lesion. Noting that the patient or guardian was informed and consented protects the office from a later “no one told me it would turn black” complaint. It is a clinical and patient-relations note more than a billing one, but it belongs in the record.
A one-line narrative on the claim, naming the tooth and the active lesion arrested with SDF, helps the carrier process it against the right benefit and the per-tooth frequency edit.
FAQs
- What is the dental code for silver diamine fluoride (SDF)?
- D1354, billed one tooth at a time, when SDF is applied to arrest an active cavity. The code is scoped as an interim measure: SDF buys time on an active lesion and is not a final restoration. The code follows the clinical purpose, not the product. If the same SDF is applied to a sound, high-risk surface for prevention, that is D1355, the caries-preventive medicament code.
- What is the difference between D1354 and D1355?
- Clinical intent on the treated tooth. D1354 arrests an active carious lesion that already exists. D1355 is preventive, applied to a sound surface for primary prevention or remineralization in a high-caries-risk patient. Both are per-tooth codes and both can involve SDF, which is why they get mixed up. The chart note has to make the intent clear: an active cavity on the treated tooth supports D1354, and a sound at-risk surface supports D1355.
- Is D1354 billed per tooth or per visit?
- Per tooth. SDF applied to four active lesions on four teeth in one appointment is four units of D1354, each tied to its own tooth number and documented separately. The topical fluoride codes D1206 (varnish) and D1208 (gel or foam, excluding varnish) work the opposite way and are reported once per visit. Posting D1354 once for a multi-tooth SDF visit underbills the work; posting topical fluoride per tooth overbills it.
- Does insurance cover D1354 for silver diamine fluoride?
- It depends on the plan, and coverage runs Medicaid-first. Many state Medicaid and CHIP programs cover D1354, often with a per-tooth lifetime cap (two applications per tooth is a common limit) and sometimes an age restriction. Commercial plans are uneven: some cover it as a preventive benefit, some only for children, and some not at all, so verify the specific plan before treatment. When the plan excludes it, D1354 is typically a low-cost patient-pay procedure, but on participating Medicaid plans confirm the patient-billable rules before charging anyone.
- Can I bill D1354 and a topical fluoride at the same visit?
- Often yes, because they are different procedures, but reimbursement is plan-dependent. D1354 arrests an active lesion on a specific tooth; D1206 (fluoride varnish) or D1208 (other topical fluoride) is a whole-mouth preventive application reported once per visit. Some plans bundle preventive services or limit how many preventive codes pay per visit. Report each procedure performed and documented, then set fee expectations against the plan's bundling rules.
- Is D1354 only for baby teeth?
- No. D1354 applies to any tooth with an active, non-symptomatic carious lesion, primary or permanent. SDF is common in pediatric care because it arrests decay without the drilling and anesthesia that young or pre-cooperative patients tolerate poorly, and it is used in geriatric and special-needs care for the same reason. The code is not age-restricted, but plan coverage may be: some carriers cover D1354 only up to a certain age, which is a benefit limitation, not a coding rule.
Related codes
Need help billing this code?
We handle D1354 claims daily.
If your team is spending time on denials, narratives, or carrier follow-up for this code, our dental insurance verification service can take it off your plate. We submit the claims, post what comes back, and follow up on anything unpaid.
“Claims, posting, denials, all of it gets handled, and it costs far less than hiring another employee. My front desk got hours of their week back, and honestly I just don't think about billing anymore.”
CDT codes are maintained by the American Dental Association. This page is an editorial billing guide, not the official ADA code descriptor. Verify current coverage policies with each carrier before submitting claims.