D3110 is the CDT code for a direct pulp cap, a medicated dressing placed directly on an exposed pulp to keep it alive.
- When to use: The pulp was actually exposed by caries removal or trauma, and the dentist dresses the exposure to keep the pulp vital.
- When not to use: A near exposure with no pulp showing is D3120, removing the coronal pulp is D3220, and an interim restoration placed before definitive treatment is D2940.
- Billing note: Most plans treat a same-day pulp cap as a base or liner bundled into the filling, so chart the exposure and check the contract before billing the patient.
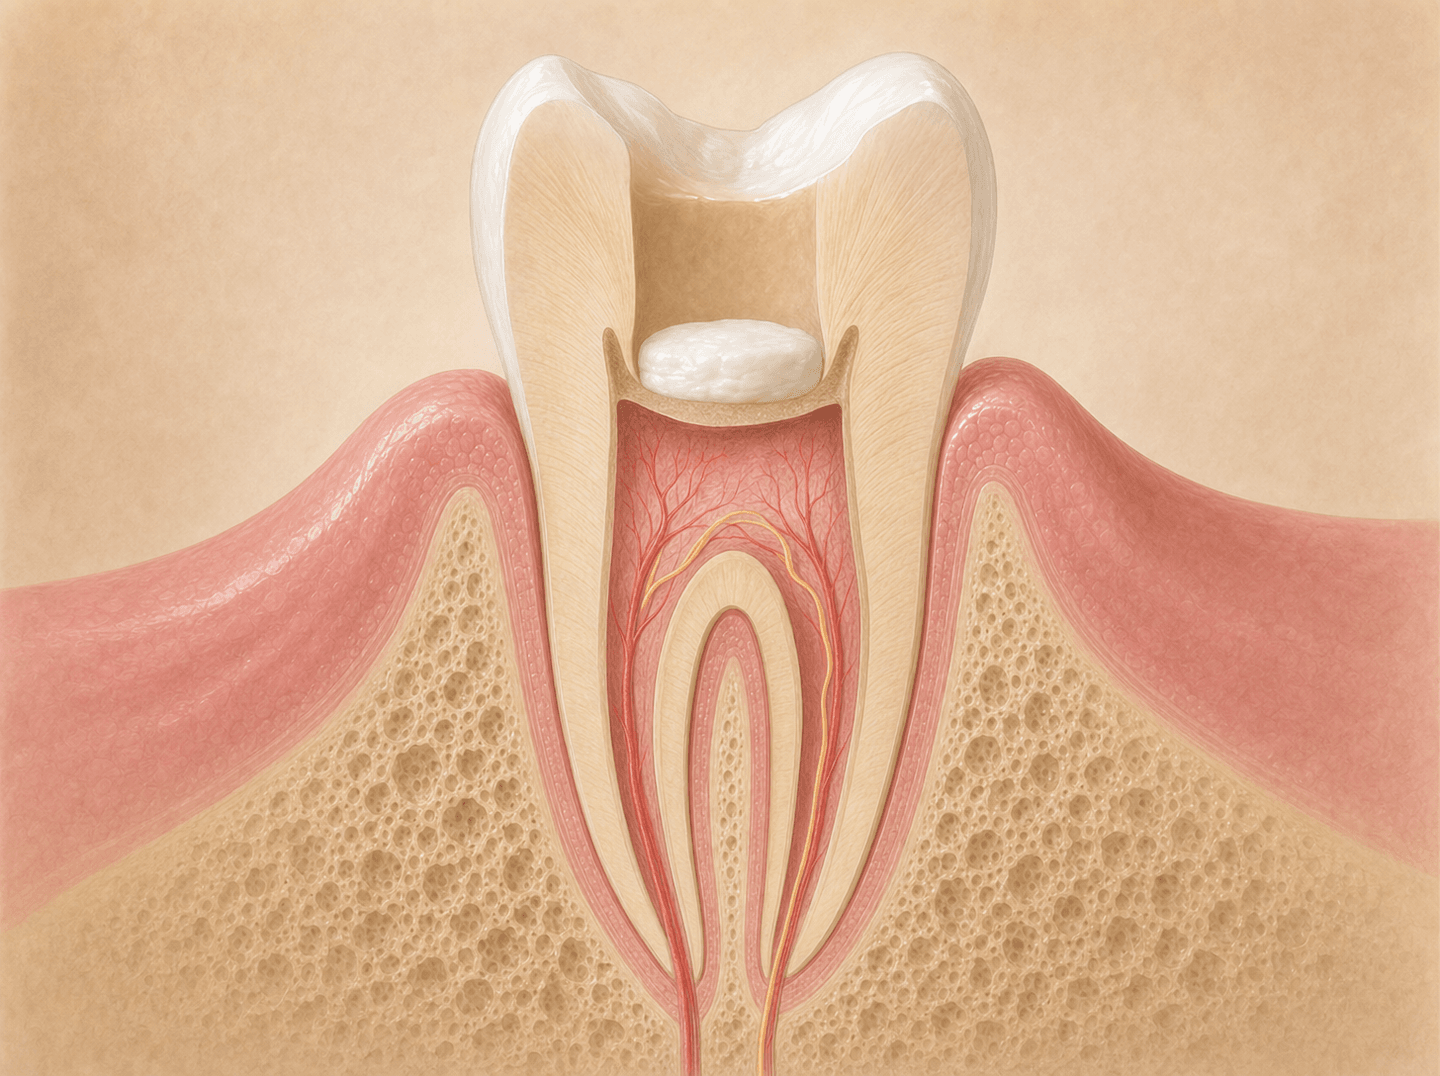
What D3110 covers
D3110 reports a direct pulp cap. The pulp is exposed during caries removal or by trauma, and rather than open the tooth for endodontic treatment, the dentist places a medicated dressing, usually calcium hydroxide or a similar material, directly on the exposed pulp to protect it and keep it vital. The goal is to avoid root canal therapy by letting the pulp heal under the dressing.
The word that matters is “exposed.” A direct cap is placed on pulp tissue you can see.
The code excludes the final restoration. D3110 reports the cap only; the filling or crown over it is billed under its own code.
D3110 does not cover:
- A cap over a pulp that was nearly exposed but still covered. That is the indirect cap, D3120.
- A base or liner placed for sensitivity in a routine cavity with no exposure. That is part of the restoration.
- Removing the coronal pulp. That is a therapeutic pulpotomy, D3220.
- An interim direct restoration placed to calm a symptomatic tooth before definitive treatment. That is D2940.
D3110 versus D3120
These two get swapped constantly. The axis is pulp exposure, and nothing else:
- D3110, direct. The pulp is exposed. The dressing sits on pulp tissue.
- D3120, indirect. The pulp is not exposed. A thin layer of dentin or intentionally retained caries still covers it, and the dressing goes over that layer.
If the dentist could see or touch pulp, it is direct. If the dentist stopped short of the pulp on purpose to avoid an exposure, it is indirect. Pull the operative note before you pick the code, and make sure the chart states the finding, because the carrier cannot tell which one you did from the code alone.
D3110 versus a base or liner
A base or liner is placed under a restoration on a tooth with no pulp exposure, to insulate or soothe the prep. A direct pulp cap is placed on an actual exposure to keep the pulp alive. The clinical difference is real even when the payment policy erases it.
The documentation is what protects the claim. If the note never mentions an exposure, the carrier reads the cap as a liner and bundles it, and an appeal has nothing to stand on. The chart needs to say the pulp was exposed and how.
The bundling reality
When a direct pulp cap and the final restoration go in at the same visit, most carriers consider the cap a base or liner. Bases and liners are included in the restorative fee, so the plan pays for the filling or crown and nothing extra for D3110. The denial usually reads as “inclusive to” or “considered part of” the restoration.
This is plan language, not a statement about whether the cap was necessary. Two consequences follow:
- Whether you can bill the patient the cap fee depends on the contract. Some participating-provider agreements bar balance-billing for a bundled procedure. Read the plan before you decide.
- A narrative helps less than it does on a necessity denial, because the carrier is applying a payment policy, not questioning the clinical work. If the contract is silent on the cap, a narrative plus an appeal is worth a try.
Documentation that supports the claim
The claim and chart should show:
- That the pulp was exposed, and the cause (caries removal or trauma).
- The capping material used.
- That the pulp remained vital, with no indication for endodontic therapy.
- The tooth number and surfaces.
A pre-op radiograph showing deep decay approaching the pulp supports the picture. The note that does the most work states the exposure plainly: “Pinpoint pulp exposure on the distal during caries excavation, calcium hydroxide placed directly on exposed vital pulp, tooth remained asymptomatic.” That sentence separates a documented direct cap from what looks like a liner.
Example case
A 34-year-old patient has deep decay on tooth #14. During caries removal, the dentist encounters a small pulp exposure. The pulp is vital with no history of spontaneous pain, so the dentist places calcium hydroxide directly on the exposure and places a composite restoration over it the same day.
Billing steps:
- Code D3110 for the direct cap and the appropriate composite code for the restoration, here a posterior composite from the D2391 series, by surface count.
- Document the exposure, the material, and the vital pulp in the chart.
- Submit and watch the EOB. The cap may bundle into the restoration as a base or liner.
- If the cap bundles, check the contract before deciding whether the patient owes the fee.
- If the plan does not address the cap and the exposure is clearly documented, appeal with the narrative.
FAQs
- What makes D3110 different from D3120?
- Pulp exposure. D3110 is the direct cap, placed when the pulp is actually exposed and the dressing sits on pulp tissue. D3120 is the indirect cap, placed when the pulp is nearly exposed but still covered by a thin layer of tooth structure or remaining caries. Coding the wrong one is the most common pulp-cap error.
- Why did the carrier pay nothing for the pulp cap?
- Because most plans treat a pulp cap placed at the same visit as the final restoration as a base or liner, which is part of the filling or crown and not a separate benefit. This is plan language, not a clinical judgment. Whether the patient can be billed the cap fee depends on the contract, so check it before writing off or balance-billing.
- Does D3110 include the filling or crown over it?
- No. The descriptor excludes the final restoration, so D3110 reports only the cap and the filling or crown is billed under its own code. That separation is also why so many carriers fold the cap back into the restoration at adjudication.
- What should the chart show to support D3110?
- That the pulp was exposed, how (caries removal or trauma), the capping material used, and that the pulp stayed vital. A note that just says a pulp cap was placed, with no mention of an exposure, reads like a base or liner and invites a bundling denial.
- Can I bill D3110 and a pulpotomy on the same tooth?
- Not for the same event. A direct pulp cap preserves the whole vital pulp by dressing the exposure; a therapeutic pulpotomy, D3220, removes the coronal pulp and treats the radicular pulp. The chart should support whichever one was actually performed.
Related codes
Need help billing this code?
We handle D3110 claims daily.
If your team is spending time on denials, narratives, or carrier follow-up for this code, our outsourced dental insurance billing service can take it off your plate. We submit the claims, post what comes back, and follow up on anything unpaid. Already sitting on older claims that never paid? Our AR cleanup project works the backlog.
“Claims, posting, denials, all of it gets handled, and it costs far less than hiring another employee. My front desk got hours of their week back, and honestly I just don't think about billing anymore.”
CDT codes are maintained by the American Dental Association. This page is an editorial billing guide, not the official ADA code descriptor. Verify current coverage policies with each carrier before submitting claims.