D7951 is the CDT code for a sinus lift done through a window cut in the side wall of the upper jaw.
- When to use: Very little bone remains under the sinus and a large vertical gain is needed for an upper posterior implant.
- When not to use: A lift through the ridge crest is D7952, a ridge graft outside the sinus is D7950, and a socket graft is D7953.
- Billing note: Verify medical and dental benefits before surgery, since sinus lifts often cross to medical, and document the low residual ridge height that justified the window.
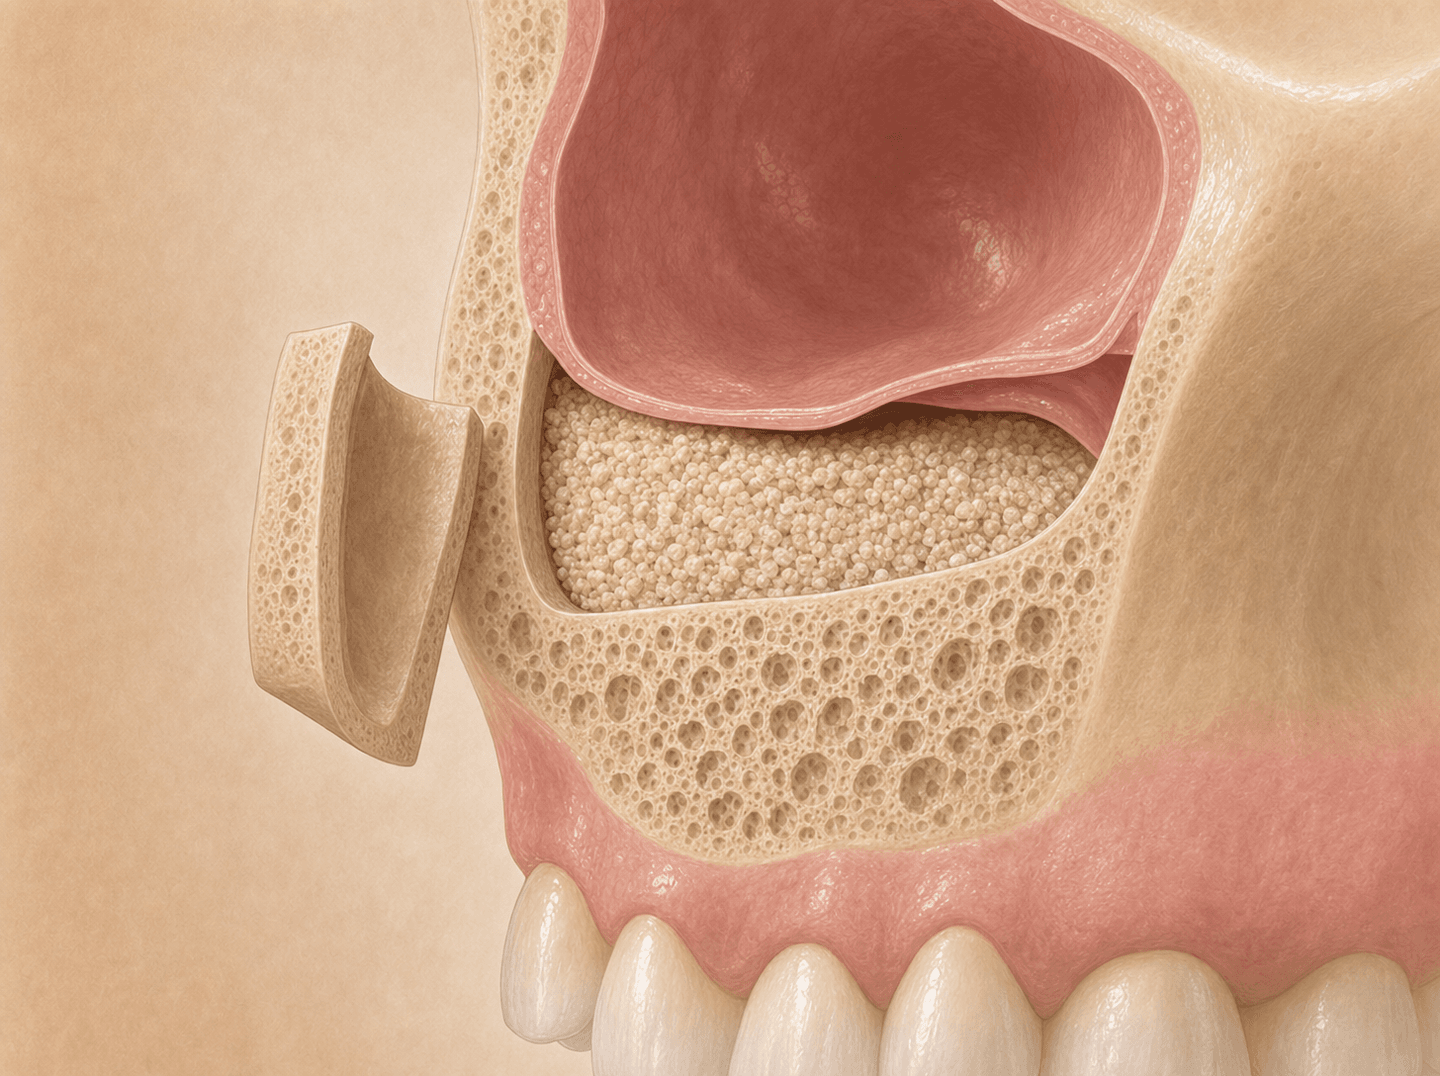
What D7951 covers
D7951 reports a sinus lift performed through the lateral open approach. The surgeon cuts a window in the side wall of the maxilla, lifts the Schneiderian membrane that lines the sinus floor, and packs bone or a bone substitute into the space underneath. This adds vertical bone height in the posterior maxilla, where the sinus often sits too low to place an upper implant.
It is the more extensive of the two sinus augmentation methods, used when a large vertical gain is needed, typically because very little native ridge height remains beneath the sinus.
D7951 does not cover:
- A sinus lift done through the crest of the ridge instead of a side window. That is D7952, the vertical approach.
- A graft that builds up the alveolar ridge itself. That is D7950.
- A graft packed into a fresh extraction socket. That is D7953.
- The implant body placement. That is D6010.
- A graft placed around the implant at the time it is seated. That is D6104.
When to bill D7951
Bill D7951 when:
- The procedure augments the maxillary sinus floor to gain vertical bone for an upper posterior implant.
- The surgeon used the lateral open approach, cutting a window in the side wall of the maxilla.
- Residual ridge height is low enough that the lateral procedure was the appropriate choice over a crestal lift.
D7951 versus D7952: the approach is the axis
Both codes have the same goal, more bone under the sinus, reached by two different routes. The distinguishing axis is the surgical approach, not the amount of graft or the implant brand.
- D7951, lateral open approach. A window is cut in the side wall of the maxilla, the membrane is lifted from the side, and graft is packed into the opened space. The more invasive procedure, used for larger vertical gains when little native bone remains.
- D7952, vertical approach. Access comes up through the crest of the ridge, through or near the implant osteotomy, and the sinus floor is raised from below and grafted. The smaller procedure, generally used when several millimeters of bone already remain.
Choosing the wrong code is the most common D7951 error. A crestal lift billed as D7951 overstates the procedure; a true lateral window billed as D7952 understates it. The carrier reads the approach from the operative note, so the narrative has to match the code. On D7951, carriers tend to want documentation, usually minimal residual ridge height, that supports choosing the open approach.
D7951 versus the ridge and socket grafts
The defect location separates sinus augmentation from the other grafts on an oral surgery ledger. D7951 and D7952 treat vertical bone loss under the sinus in the posterior maxilla. D7950 adds height, width, or volume to the alveolar ridge outside the sinus. D7953 fills a fresh extraction socket, billed per site.
If the work raised the sinus membrane, it is a sinus code. If it built up the ridge, it is D7950. If it held an open socket, it is D7953. The bone graft dental codes guide asks the sinus question before any other, so a lift never gets coded as a ridge or socket graft.
Medical crossover
Sinus augmentation is one of the dental procedures most likely to cross to medical, so billing starts with coordination, not with picking a single plan.
Many practices submit the medical claim first and bill dental for any remaining benefit. Whether medical pays depends on the diagnosis and the plan: some medical carriers cover sinus augmentation tied to a recognized condition, others treat it as elective. On the dental side, a number of plans exclude sinus augmentation as implant-related, the same way they exclude ridge augmentation done to enable an implant.
There is no universal answer. Verify both benefits before treatment, confirm which carrier is primary, and settle the patient’s financial responsibility before the surgery date.
Example case
A patient needs two implants in the upper left posterior, but a CBCT shows only about three millimeters of bone beneath a low sinus floor, not enough to anchor implants and too little for a crestal lift. The surgeon plans a lateral window sinus augmentation, with implants staged six months later once the graft consolidates.
Billing steps:
- Verify medical and dental benefits for sinus augmentation, and determine which is primary for this case.
- Write the narrative naming the lateral open approach, the residual ridge height that ruled out a crestal lift, the graft material, and the planned implants.
- Submit to medical first if it is primary, then dental for any remaining benefit. Code D7951 on the dental claim with the CBCT attached.
- Do not bill the implants or any D6104 graft now. Those are separate procedures at the staged implant visit.
- Reconcile both EOBs and bill the patient any balance the plans did not cover, knowing many plans treat this as implant-related.
FAQs
- What is the difference between D7951 and D7952?
- The surgical approach. D7951 is the lateral open approach: the surgeon cuts a window in the side wall of the maxilla, lifts the sinus membrane, and packs graft underneath. D7952 is the vertical approach, entering up through the crest of the ridge at the implant site. D7951 is the more extensive procedure, used when a large vertical gain is needed; D7952 is the crestal lift used for smaller gains when several millimeters of bone already remain.
- Should I bill D7951 to medical or dental insurance?
- Often both, in coordination. Sinus augmentation crosses to medical more readily than most dental surgery, especially when tied to a diagnosis the medical plan recognizes. Many practices submit medical first, then dental for any remaining benefit. Coverage is plan-dependent: some dental plans exclude it as implant-related, and some medical plans treat it as elective. Verify both benefits before treatment.
- Is D7951 the same as a bone graft on the ridge?
- No. D7951 lifts the sinus membrane and grafts beneath it to gain vertical bone for an upper implant. A graft that builds up the alveolar ridge itself is D7950, and a graft packed into a fresh extraction socket is D7953. Using a ridge or socket code for sinus work is a mismatch the carrier will catch.
- Can D7951 and the implant be billed on the same day?
- Yes, when the lift and implant are done together; other times the lift is staged ahead of the implant to let the graft mature. When they are simultaneous, D7951 reports the sinus augmentation and D6010 reports the implant body; a graft placed around the implant at that visit is D6104. When staged, D7951 is billed at the sinus surgery and the implant codes come later. The carrier reads the timing from the narrative.
- What documentation does a D7951 claim need?
- A pre-op image, ideally a CBCT, showing the deficient sinus floor and residual bone height, plus a narrative naming the lateral window approach, the graft material, and the planned implant. Because the lateral approach is the more invasive sinus code, carriers expect documentation, such as minimal residual ridge height, that supports choosing it over the vertical approach.
Related codes
Need help billing this code?
We handle D7951 claims daily.
If your team is spending time on denials, narratives, or carrier follow-up for this code, our outsourced dental insurance billing service can take it off your plate. We submit the claims, post what comes back, and follow up on anything unpaid. Already sitting on older claims that never paid? Our AR cleanup project works the backlog.
“Claims, posting, denials, all of it gets handled, and it costs far less than hiring another employee. My front desk got hours of their week back, and honestly I just don't think about billing anymore.”
CDT codes are maintained by the American Dental Association. This page is an editorial billing guide, not the official ADA code descriptor. Verify current coverage policies with each carrier before submitting claims.